How this prediction is made
Not projections copied from plan filings. Six classes of signal go in. One explainable forecast per payer comes out.
- Benefit design
- True Plan Value
- Enrollment history
- Service area changes
- Broker commissions
- Market conditions
*Accuracy reflects historical performance of our enrollment prediction models and varies by segment, geography and forecast horizon. Predictions account for broker commissions as of 7 October 2026.
✓ Our record
Everyone forecasts. Almost nobody publishes a score.
Our enrollment models have run at 91.2% accuracy against what actually happened, and we forecast all three enrollment windows, not just the one everybody watches.*
*Accuracy reflects historical performance of our enrollment prediction models. It varies by segment, geography and forecast horizon, so a single figure should be read as a track record, not a guarantee for any one plan or market.
01 Footprint
What did pulling out of markets actually cost?
The 8 largest payers are forecast to release ~630K members. They call it refinement. The arithmetic calls it share, and KFF's county counts show exactly where they went.
Who gains and who loses members by February 2027
Our xAI forecast of each payer’s member change from September 2026. Bigger tile, bigger change. Actual results land in January.
Devoted Health
enters 342 counties
UnitedHealth Group
exits 34 counties
Humana
exits 61 counties
Centene
exits 183 counties
Health Care Service Corp.
exits 472 counties
BCBS Michigan
exits 194 counties
County exit and entry counts from our platform, 7, October 2026. Member change is our forecast. County definitions differ between sources. *Historical accuracy of our enrollment prediction models; it varies by segment, geography and forecast horizon.
So what. A footprint decision is a membership decision with a two-year delay. The county map shows who moved. It does not show what the move costs.
02 Share
Those members do not disappear. They move.
Scale is not protecting share this year. Devoted Health alone is forecast to add ~455K members, close to doubling, on a 2027 footprint of 740 plans.
Forecast member change by payer, rankedxAI forecast
Values are predicted February 2027 membership, rounded to thousands (K). Bars show the direction and relative size of each payer’s forecast change from September 2026 actual. Payers grouped as growing, holding close to flat, or pulling back.
So what. The members leaving the nationals are not leaving Medicare Advantage. They are choosing a competitor you may not have modelled.
03 The market
Is Medicare Advantage really flat in 2027?
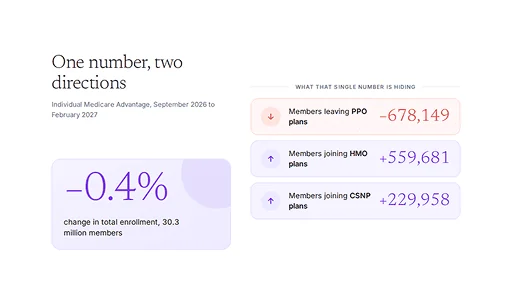
No. Two large movements cancel each other out, and only one of them is in your book. CMS publishes one national projection. We forecast 161 payers separately.
So what. A flat headline is the least useful number in the market this year. Nobody competes at the national level.
04 The shift
Where are members actually moving?
Out of PPOs. Into HMOs and CSNP plans. ~680K members change plan type, the largest rotation in years.
Where the members go, by plan type and special needs typexAI forecast
Plan-type and special-needs views are drawn from separate cuts of the landscape file and do not sum to the same total.
So what. If your 2028 bid assumes the PPO book holds its shape, the forecast disagrees with you by ~680K members.
05 True Plan Value
What is a plan actually worth to a member?
True Plan Value is the benefit value a member realises above traditional Medicare, per member per month. Across the 20 largest payers it has fallen every single year since 2024.
Average relative True Plan Value, 20 largest payers
Relative view: earlier years are restated under current-year policy, so the movement shown is benefit-driven rather than a change in the rules. Figures are $PMPM, risk adjusted, Part C plus Part D plus Part B giveback.
Held their value
Cut the deepest
So what. How deeply a payer cut tells you almost nothing about what happened to its membership. Devoted cut value by a third and is still forecast to grow 86%. True Plan Value measures where you stand. It does not predict where you land, which is why the two are separate tools.
06 Benefit value
Does higher value go with growth?
On average the payers sitting higher on value are the ones our model forecasts to grow. The link is real but loose, so value is one input among several, never a forecast on its own.
Average member change by True Plan ValuexAI forecast
40 payers
40 payers
Payers with at least 20,000 members, split at the median.
Why value tilts the table but does not decide it
Whether value converts into members also depends on footprint, network and what competitors did in the same county.
So what. You cannot answer this from your own benefit sheet. The answer sits in the gap between your value and everyone else competing for the same member.
Proof from a customer
A national payer stopped guessing, and found 3,700 members
Benefit value only pays off when you know which change moves enrollment. A leading national payer used our Benefit Simulator to test 81 scenarios and 3,699 benefit permutations across 10 states before filing.
“Our enrollment predictions were subjective, lacking the hard data science needed for confident decision-making.” Chief Financial Officer, national Medicare Advantage payer
Your next move
Q3 Earnings season
UnitedHealth Group reported first. Six more payers follow.
We read each Q3 2026 earnings call next to our AEP 2027 plan data. The UnitedHealth Group analysis is live now. The other payers follow as they report, then one roundup of all seven.
Coming next
- Elevance Health
- Molina Healthcare
- Centene
- Alignment Healthcare
- CVS Health
- Humana
- Roundup of all seven
 Out now
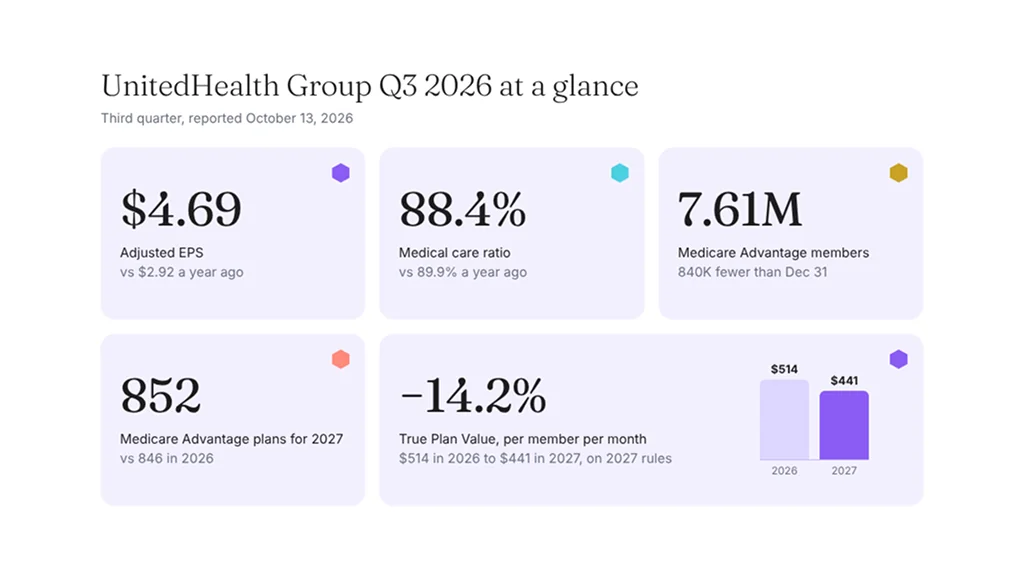
UnitedHealth Group Q3 2026 earnings: margins recover, and the 2027 Medicare Advantage map gets selective
Read the analysis →
Speak to our experts
Want this forecast for your markets?
This page is the national view. Our experts can take you through the same forecast by state, county and plan type, for your plans and your competitors, and what it means for your 2028 bid.
Questions we get asked
How much will Medicare Advantage enrollment change in 2027?
We forecast 30,179,988 individual MA members in February 2027, against 30,297,955 in September 2026. That is a fall of ~118K members, or 0.4%. The headline is close to flat, but the composition changes significantly.
Why is Medicare Advantage PPO enrollment falling in 2027?
We forecast PPO enrollment falling 678,149 members, or 6.7%, while HMO enrollment rises 559,681. Several national carriers reduced PPO footprints for 2027, describing the change as footprint and product refinement on recent earnings calls.
Are CSNPs growing in 2027?
Yes. We forecast CSNP enrollment rising 229,958 members, or 12.6%, the fastest growth of any segment. D-SNP is broadly stable and I-SNP edges lower. CSNP growth does not offset the general enrollment decline of 360,893.
Has Medicare Advantage True Plan Value fallen for 2027?
Yes. Across the 20 largest payers, average relative True Plan Value fell from 577 in 2024 to 428 in 2027, a drop of 25.8%, and all twenty deliver less True Plan Value in 2027 than in 2024. True Plan Value is the benefit value a member realises above traditional Medicare on a per member per month basis.
Which Medicare Advantage payers are forecast to gain the most members in 2027?
Devoted Health is forecast to grow from 531,137 to 986,287 members, up 85.7% on a 740-plan footprint. Clever Care is forecast to grow 59.6%, Alignment 14.8% and SCAN 13.8%. The 8 largest payers are forecast to decline 2.9% in total.
How accurate are Medicare Advantage enrollment predictions?
Our enrollment prediction models have run at 91.2% accuracy historically, varying by segment, geography and forecast horizon. Last cycle, plan bid projections submitted to CMS indicated enrollment would decline; we forecast a broadly steady market, and the market held.
Predictions account for broker commissions as of 7 October 2026. Any changes in broker commissions or other factors during AEP may change these predictions. AEP runs 15 October to 7 December 2026; actual enrollment data follows in early 2027. County exit and entry counts are from KFF, published 9 October 2026. CMS plan projections are from the CMS press release of 28 September 2026.